

Pilonidal Sinus Care
Imagine a strand of hair behaving like a tiny splinter.
Instead of growing harmlessly on the surface, loose or broken hair can become embedded in the skin at the top of the cleft between the buttocks.
The body recognises it as something that does not belong there.
Inflammation may follow. A small cavity can develop. Infection can produce pus. And over time, a narrow tunnel or sinus tract may form beneath the skin.
Understanding that hidden tunnel is the key to understanding pilonidal sinus.
In the News
Sometimes there is only one opening.
Sometimes several openings beneath the skin communicate with one another.
This is pilonidal sinus disease.
It commonly develops around the tailbone region and is particularly associated with factors such as coarse body hair, prolonged sitting, a deep buttock cleft and obesity.
What looks like a tiny hole on the surface can therefore hide a larger problem underneath.
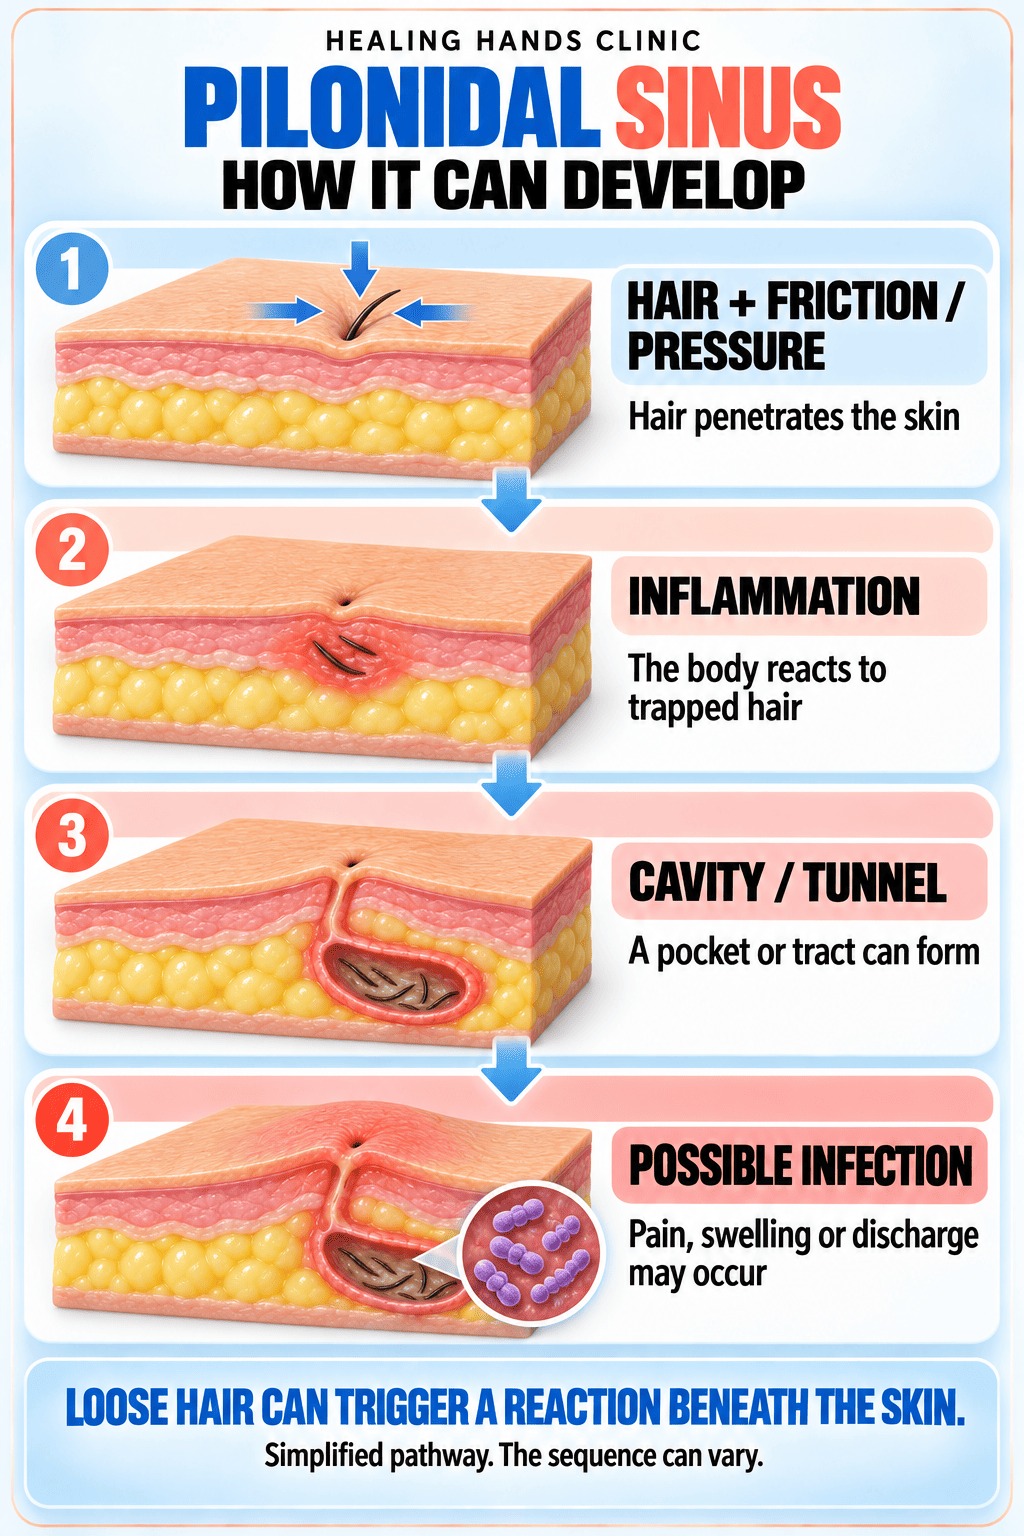
There is rarely one single cause.
Several factors can make it easier for loose hair to collect in the cleft and penetrate the skin.
These include:
The condition is more common in males, although women can develop it too.
The important point is this:
Hair may be the trigger, but the shape and environment of the cleft can help determine whether the problem keeps returning.
A pilonidal sinus can remain quiet for some time.
A person may notice only a tiny pit or opening near the tailbone.
When inflammation or infection develops, the picture changes.
Common symptoms include:
A useful way to think about the condition is:
The opening is what you see.
The tract beneath it is what needs to be understood.
Diagnosis is usually straightforward.
A doctor takes a history of the pain, swelling, discharge and previous episodes and then carefully examines the area around the buttock cleft and tailbone.
The examination helps establish:
For many patients, history and clinical examination are sufficient.
About Pilonidal Sinus
Pilonidal disease became famously associated with soldiers who spent prolonged periods sitting and travelling in military vehicles.
The nickname "Jeep disease" captures one part of the problem: prolonged sitting, pressure, and friction around the buttock cleft can contribute to conditions that lead to pilonidal disease.
But driving itself is not the disease.
The real story is the interaction between hair, skin, friction, and anatomy.
One patient may have a small, quiet pit.
Another may arrive with a painful abscess.
A third may have several openings and branching tracts after repeated infections or previous operations.
That is why treatment should not begin with the question:
"Which operation should I have?"It should begin with:
"What type and extent of pilonidal disease do I have?"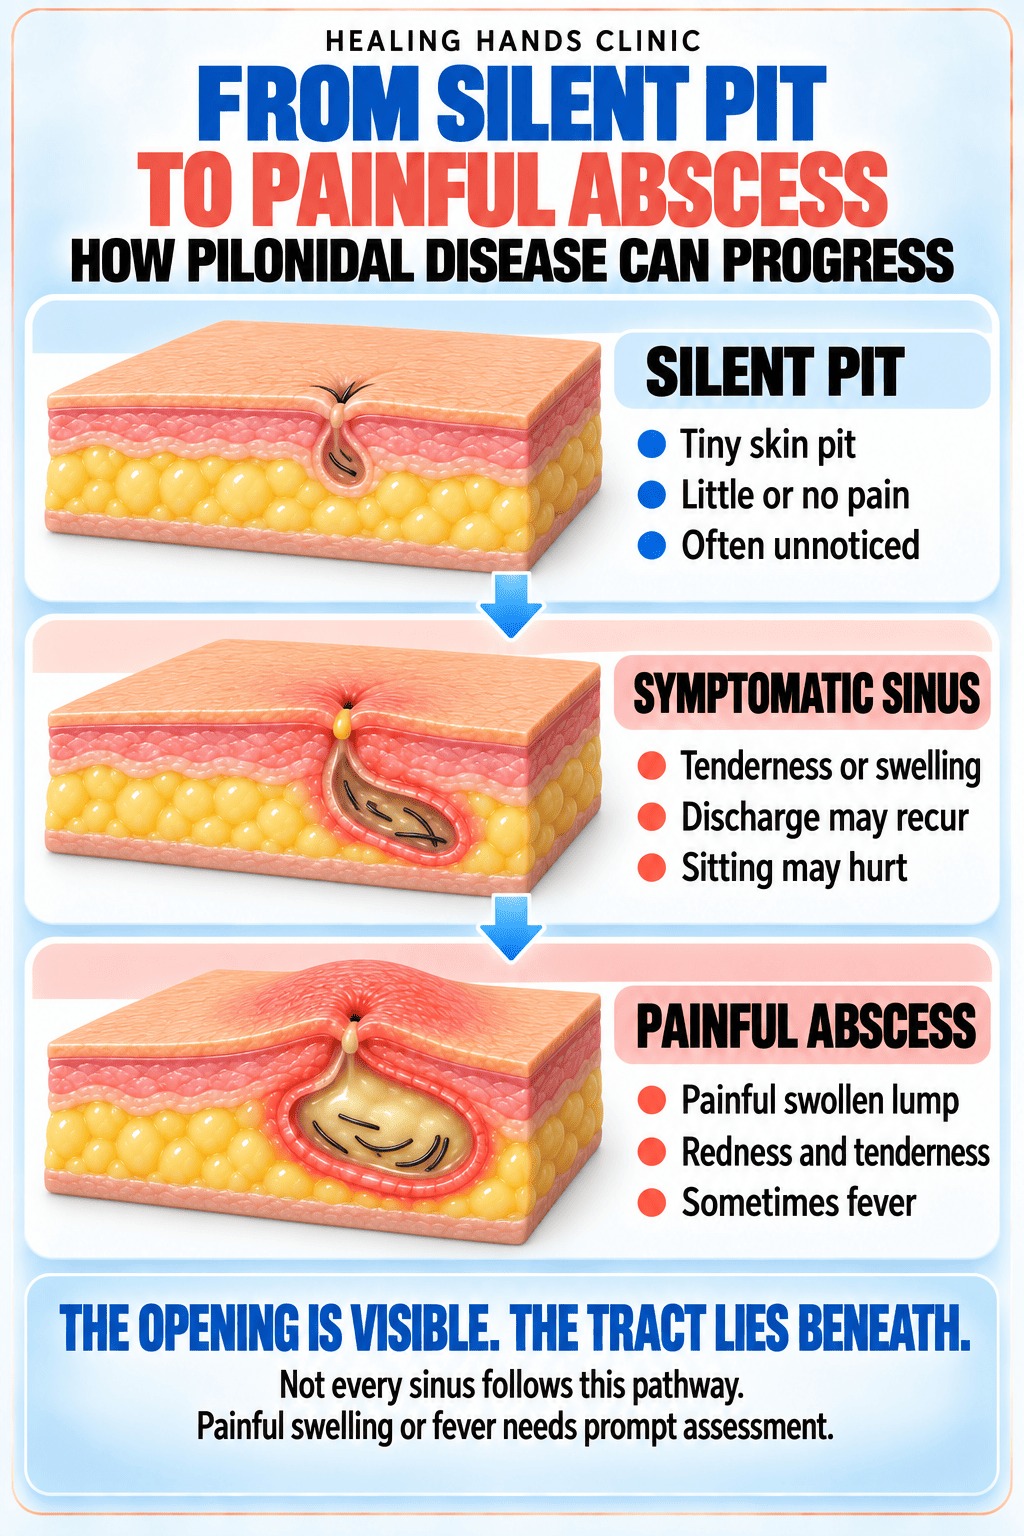
Treatment Principle
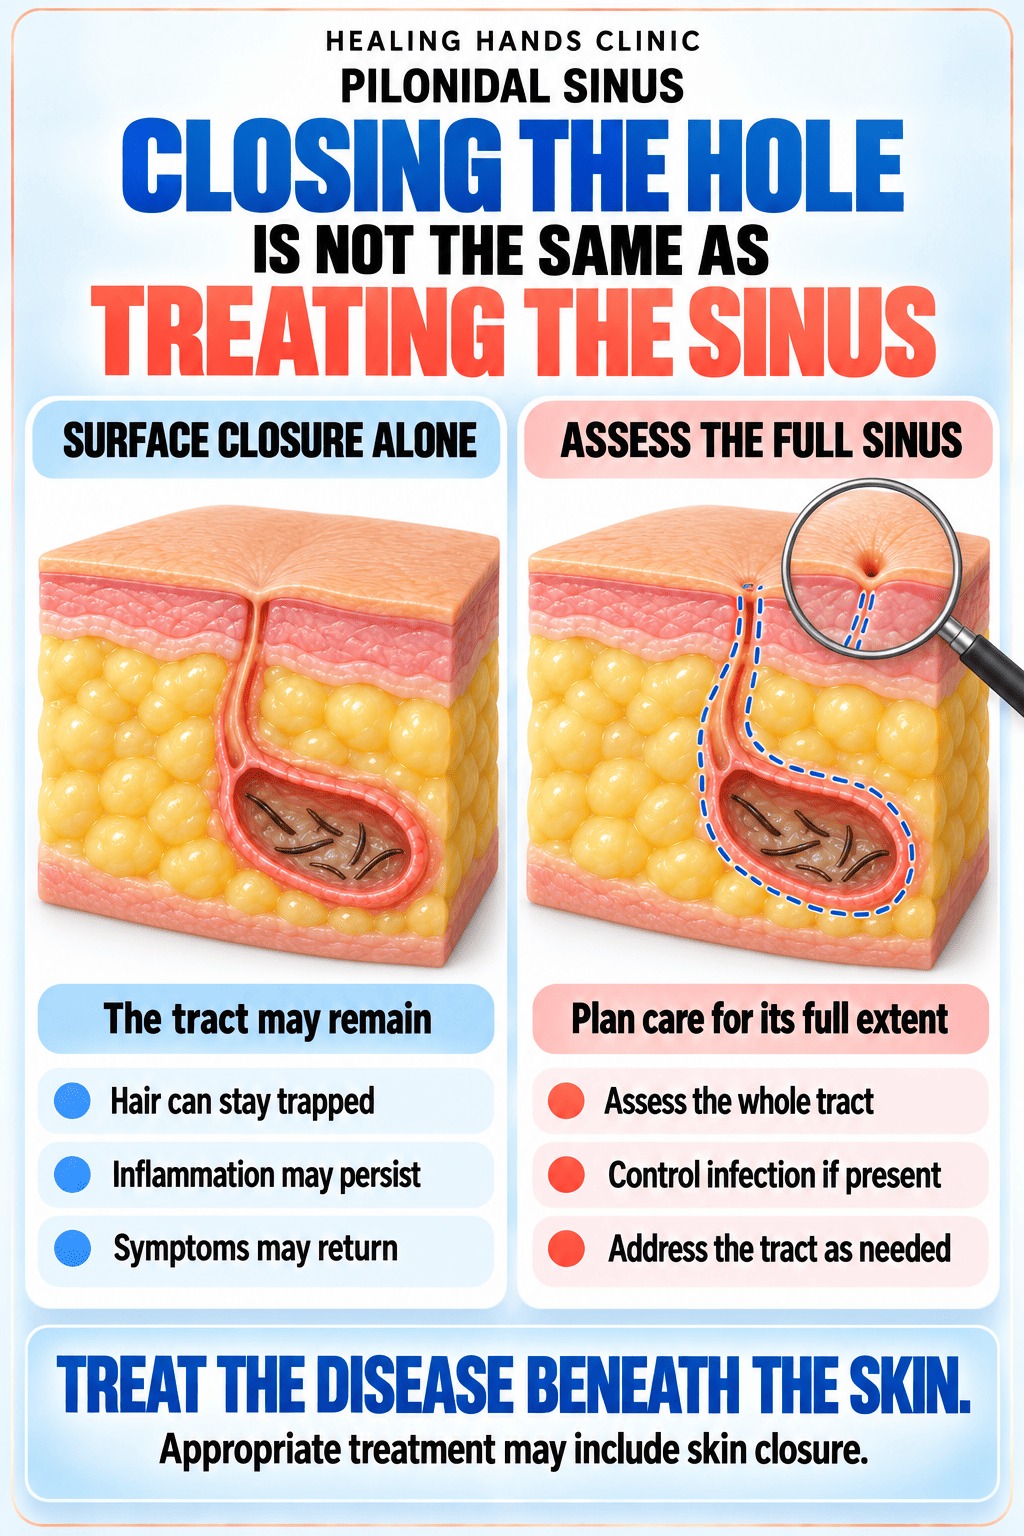
A tiny skin opening can be misleading.
The visible opening may represent only the entrance to a tract beneath the skin.
Treatment therefore depends upon whether the sinus is:
The objective is to control infection where present, deal appropriately with the sinus tract and create conditions that reduce the likelihood of another episode.
Comprehensive Care
Treating the Tunnel Through a Smaller Opening
Healing Hands Clinic uses Laser Pilonidoplasty (LPP) as a minimally invasive approach in selected patients.
Instead of creating a large open wound, the aim is to access the diseased tract through a much smaller opening.
Any collection or infected material is dealt with, and a laser fibre is introduced into the sinus tract.
Laser energy is then delivered along the tract.
The difference can be visualised simply:
Remove the tunnel together with a larger surrounding area.
Enter the tunnel and treat it from within while limiting the external wound.
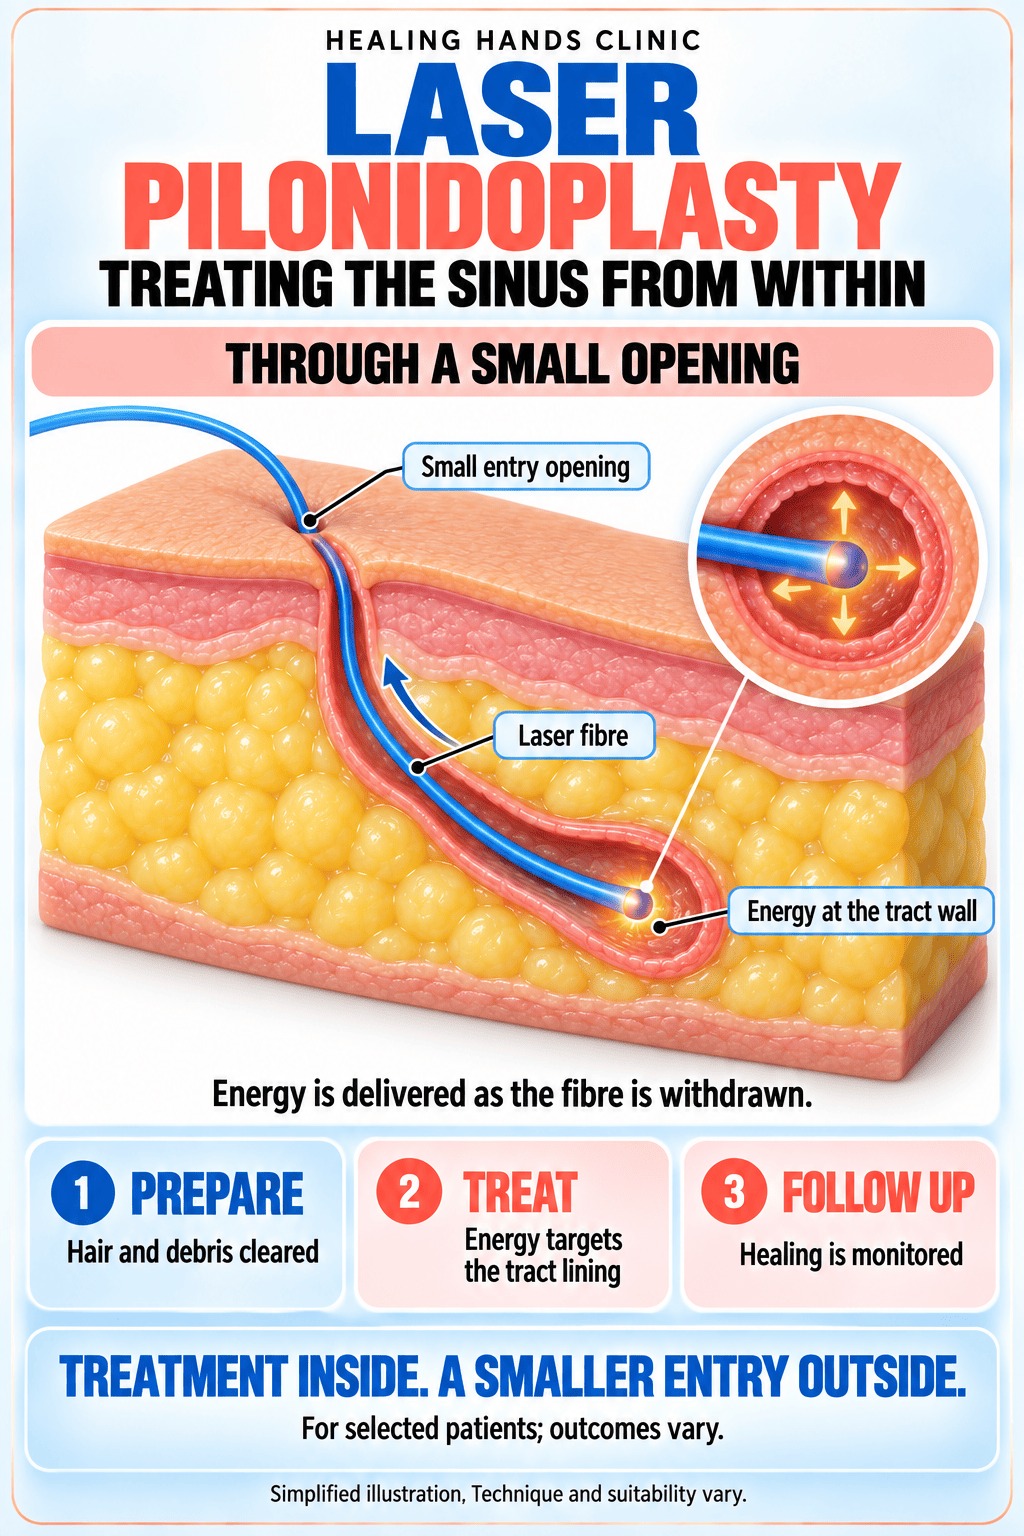
Potential advantages of a minimally invasive approach can include a smaller wound and earlier return to routine activity in appropriately selected patients.
But laser is a tool, not a guarantee.
The important question is not whether laser sounds more advanced.
It is whether a minimally invasive approach is appropriate for the extent, anatomy and complexity of that particular patient's disease.
A pilonidal sinus that is not causing active infection or troublesome symptoms may not always require immediate surgery.
Care may include:
Hair management can involve temporary removal methods or, in selected patients, consideration of laser hair reduction.
Once recurrent pain, swelling, pus or infection develops, medical assessment becomes important.
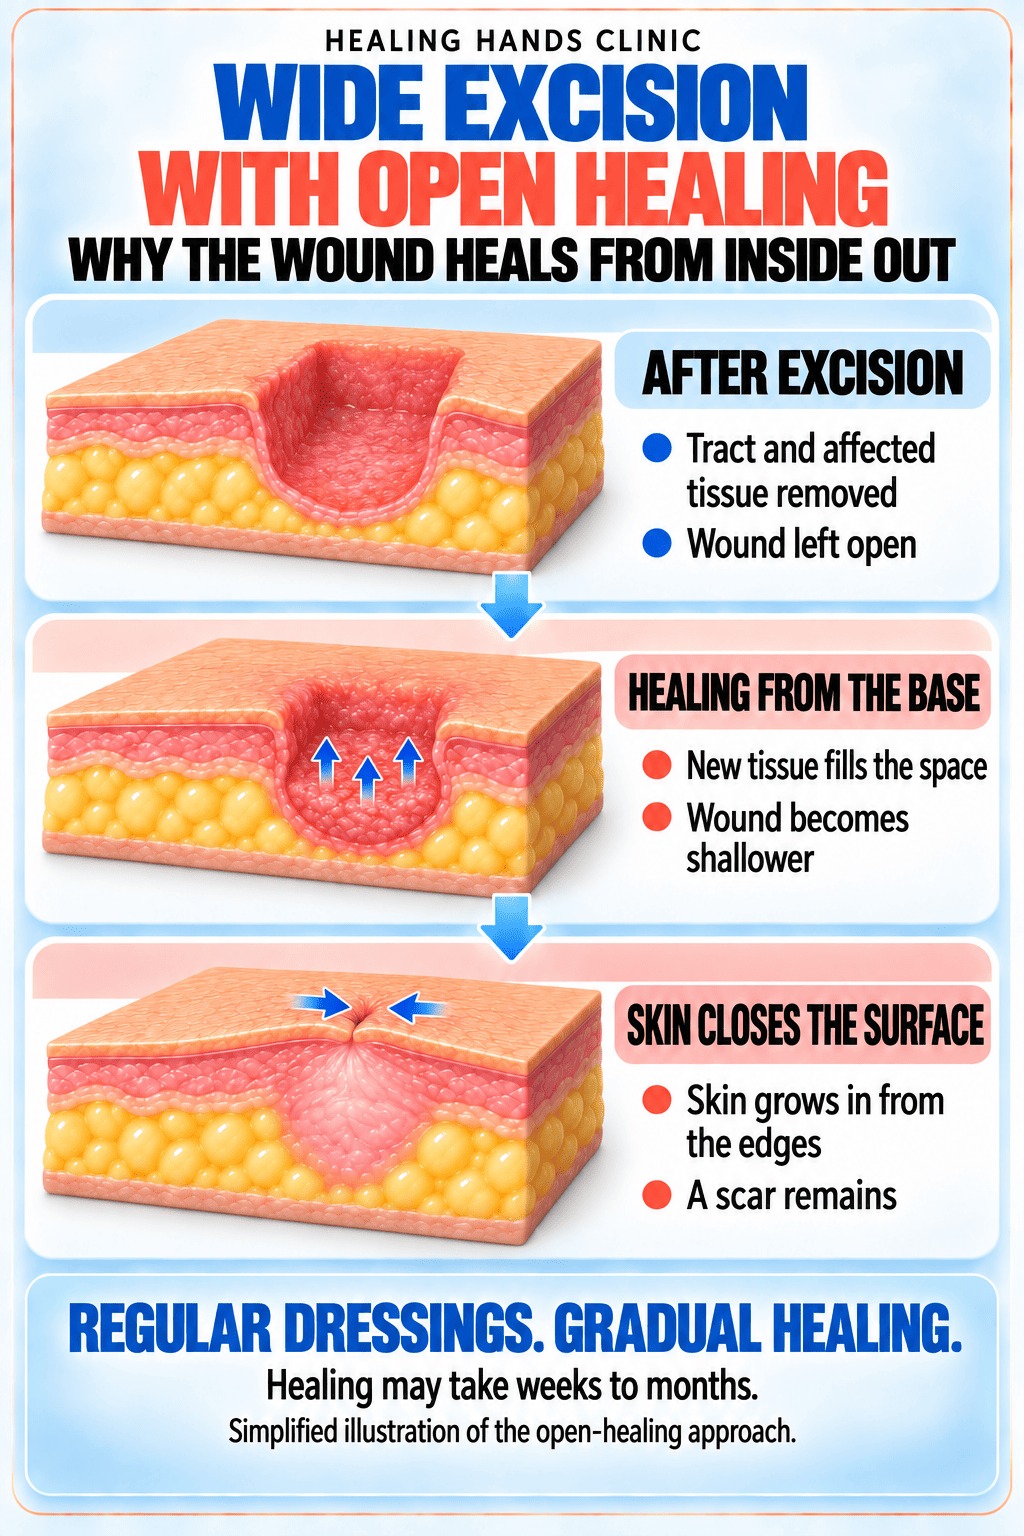
This is a traditional surgical approach.
The diseased tissue and sinus tract are removed, leaving an open wound that gradually heals from the bottom upwards.
Think of it as removing the diseased tunnel and allowing the space it occupied to rebuild itself naturally.
The trade-off is that the resulting wound can be relatively large and may require regular dressing and a prolonged healing period.
Instead of leaving the surgical wound open, the diseased tissue is removed and the wound is closed with sutures.
Where appropriate, surgeons may favour closure away from the central midline because the environment within the deep cleft can make healing more difficult.
The potential advantage is faster wound closure.
The important consideration is achieving reliable healing without infection or recurrence.
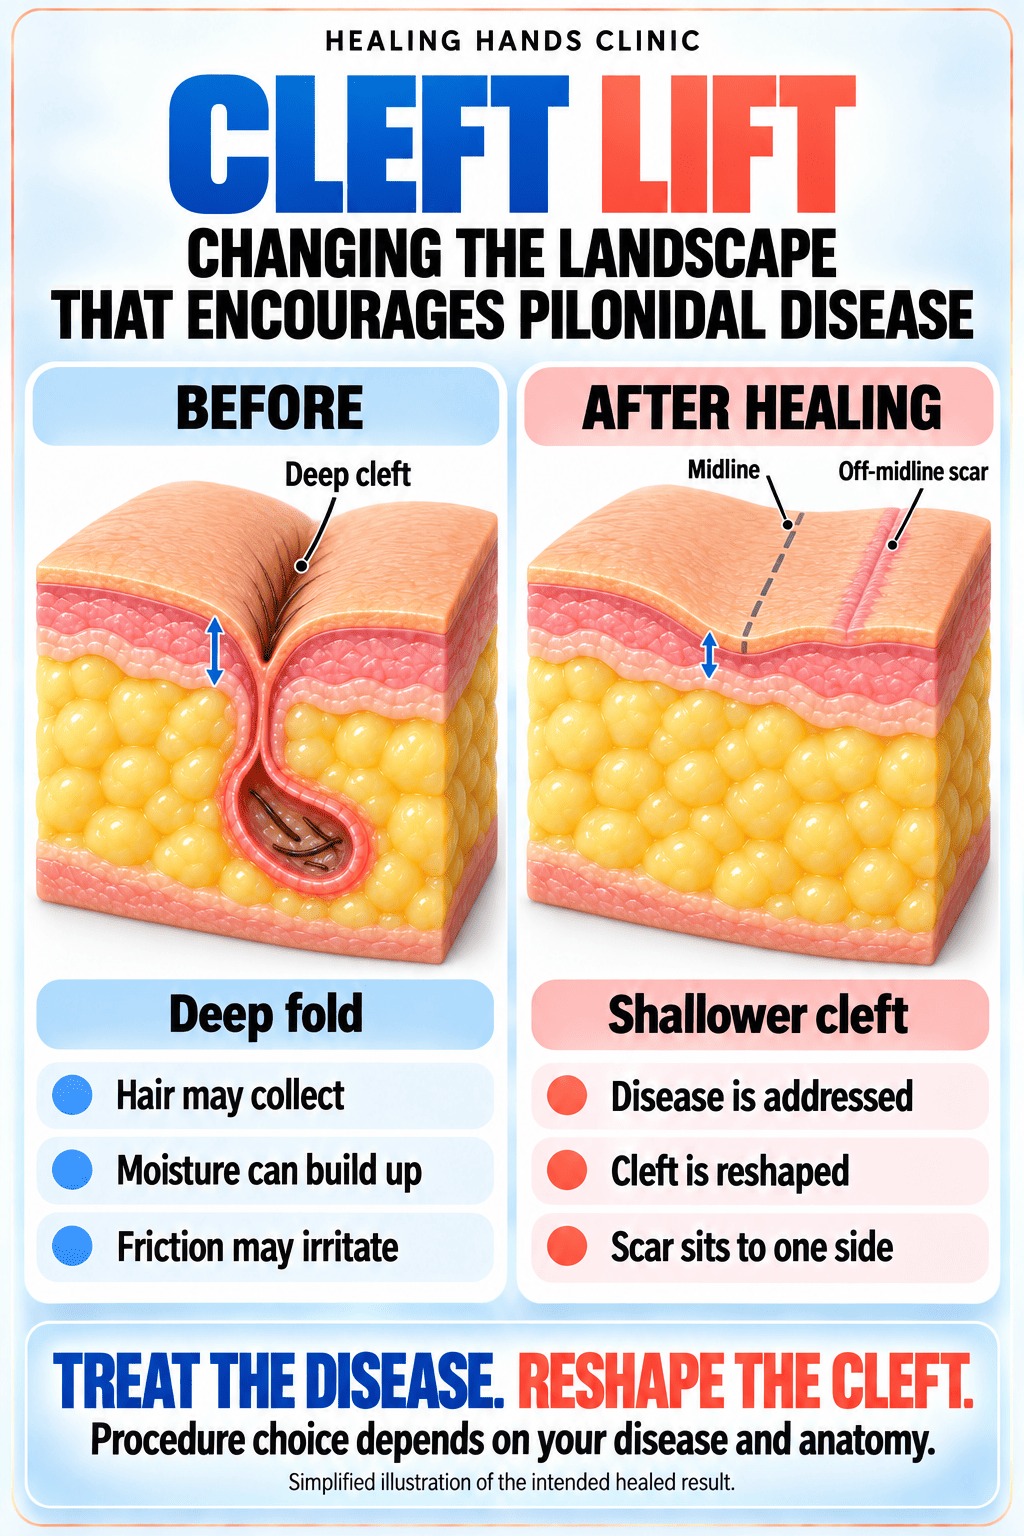
These operations address something deeper than the sinus itself: the anatomy that may be helping the disease recur.
After diseased tissue is dealt with, the surgeon reshapes or flattens the cleft and moves the final scar away from the deepest part of the midline.
Why?
A deep cleft can collect loose hair and create a warm, moist, high-friction environment.
Making it shallower can change that environment.
It is rather like redesigning a waterlogged road rather than repeatedly filling the same pothole.
For extensive or complicated disease, tissue from the neighbouring buttock may be mobilised to cover the area after diseased tissue has been removed.
Procedures such as a Limberg flap are examples.
These are larger operations and may involve a longer recovery, but they can have a role in appropriately selected complex or recurrent cases.
The operation therefore has to match the disease.
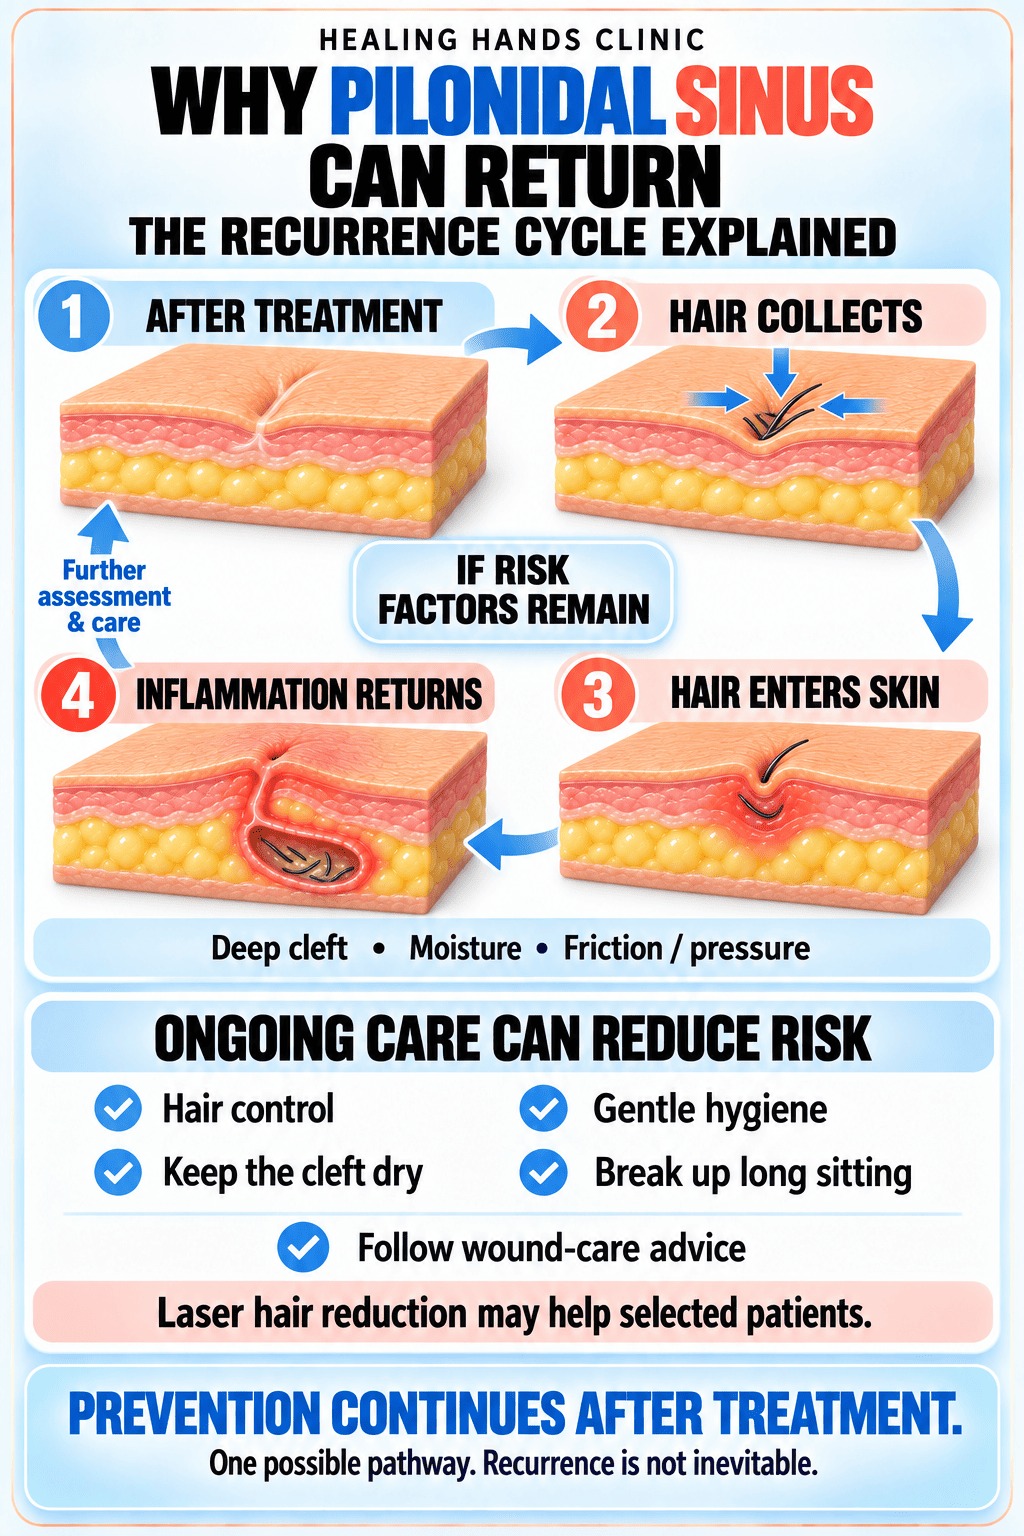
Recurrence
This is perhaps the most important question patients ask.
Removing a sinus does not necessarily remove all the conditions that helped create it.
That is why recurrence prevention extends beyond the operation itself.
Depending on the individual patient, long-term care may involve:
In selected patients, laser hair reduction may help reduce the amount and thickness of hair in the area.

A pilonidal sinus can look deceptively simple from outside.
The real challenge is understanding what lies underneath.
Healing Hands Clinic follows a disease-specific proctology approach in which treatment is planned around the extent of disease, anatomy, previous treatment and the individual patient, rather than around a single procedure.
The goal is not merely to close an opening.
It is to understand why the disease developed, how far it extends and what can be done to reduce the chance of it returning.
Frequently Asked Questions
Wound care depends upon whether the wound has been left open, sutured or treated through a minimally invasive technique.
Patients should follow their surgeon's instructions regarding washing, drying, dressings, activity and hair management rather than applying a single wound-care routine to every operation.
A pilonidal sinus is a small tunnel or cavity in the cleft of the buttocks near the tailbone, often containing trapped hair and debris. It commonly affects young adults, particularly men, and people who sit for long periods. It can become painful, infected, and discharge pus.
Recurrence is the main challenge, and is more likely after wide open excisions that leave large wounds or fail to address all the tracts. Incomplete removal, poor wound healing in the cleft, and ongoing hair entry all contribute. Minimally invasive techniques aim to reduce both recurrence and healing time.
Laser pilonidotomy is a minimally invasive laser treatment that cleans and ablates the sinus tract through a small opening, avoiding large excisions. It is associated with a small wound, faster healing, and a quicker return to normal activity than traditional open surgery.
Research at Healing Hands Clinic : Dr. Porwal published an exploratory study of laser pilonidotomy in 228 patients (Journal of Coloproctology, 2019), reporting a 96.75% success rate with a low recurrence rate of 3.24%.
Minimally invasive laser treatment usually means a small wound, simpler dressings, and a faster return to work than open excision. Recovery still varies by individual and the extent of disease, and good hygiene and hair control help prevent recurrence.
Research at Healing Hands Clinic : Dr. Porwal’s PiloKit formulation has also been studied for the management of perianal and pilonidal wounds in a prospective clinical study of 87 patients (Journal of Herbal Medicine, 2026).
Keeping the area clean and free of hair is the most important preventive measure. Hair removal in the cleft, good hygiene, and avoiding prolonged unbroken sitting reduce the chance of recurrence.
Contact your treating team if you develop:
Pilonidal disease teaches an important lesson.
Sometimes medicine cannot solve a recurring problem merely by removing its visible result.
The environment that produced it matters too.
An operation may remove or treat that tunnel.
But preventing another episode may also mean changing the conditions that allowed the process to begin.
That is why long-term management may include keeping the cleft clean and dry, controlling excess hair, avoiding prolonged pressure where practical and following appropriate postoperative care.
The smallest opening on the skin can conceal a surprisingly complicated landscape underneath.
schedule your consultation with our experts now.
Healing Hands Clinic is India’s most trusted center of excellence for proctology, specializing in advanced, minimally invasive laser treatments for anorectal conditions. Founded by Dr. Ashwin Porwal, a pioneer who introduced laser proctology to India, the clinic provides world-class, focused care for ailments like piles, fistulas, fissures, pilonidal sinus, and chronic constipation. Utilizing state-of-the-art infrastructure and modern techniques like DLPL, they prioritize treatments that provide minimal pain, negligible recurrence rates, shorter hospital stays, and quicker recovery.

Disclaimer : The information on this site should not be considered as medical advice. Please consult a doctor for determining the best procedure as well as the most appropriate for your proctological needs.



